Optimal Ferritin Range for Energy and Iron Status
Reference ranges catch disease, not the ferritin level where your body actually performs well.

Ferritin is the most misread number on a standard blood panel. The lower limit of the reference range marks the point where disease becomes undeniable, not the point where a body actually has enough iron to run well, and that difference explains why so many people with "normal" labs still feel terrible.
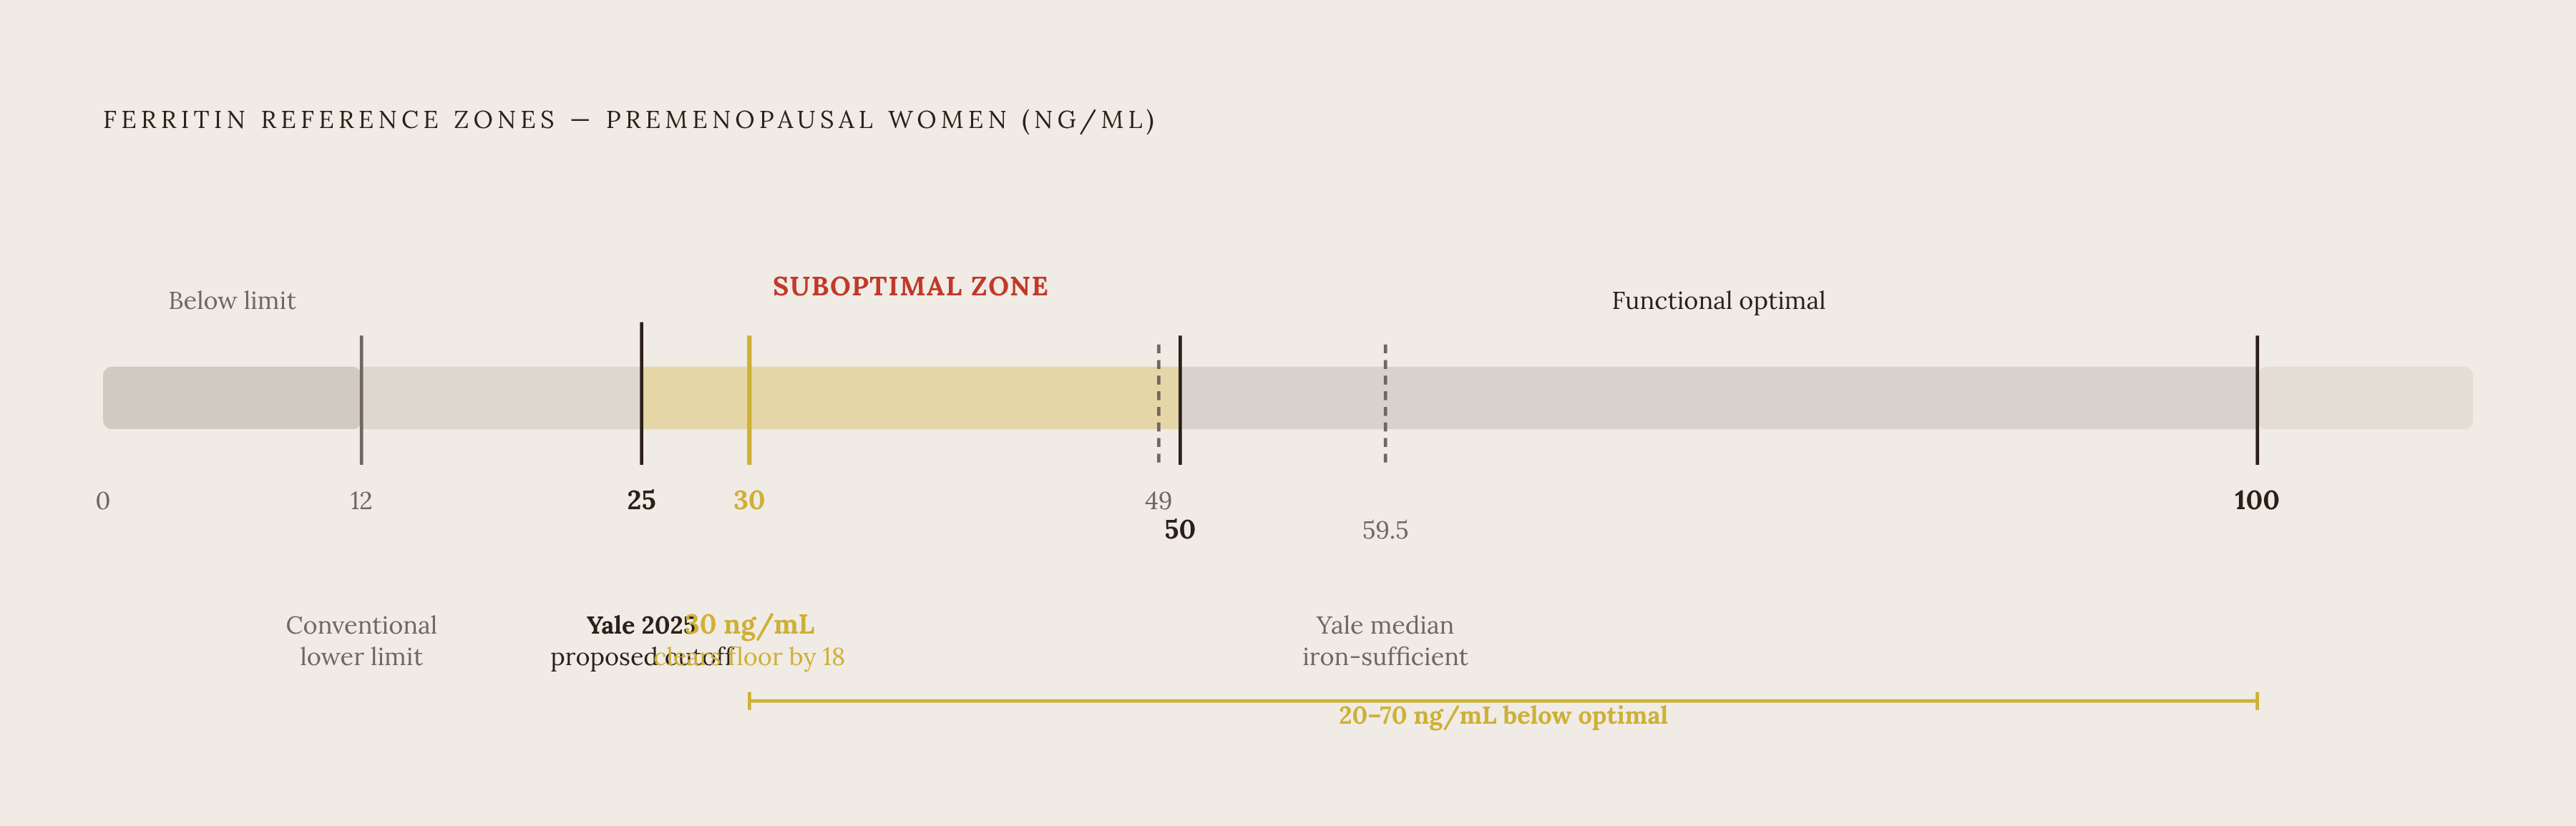
Functional medicine targets ferritin between 50 and 100 ng/mL for women and 70 to 150 ng/mL for men as the range where mitochondria, hair follicles, thyroid enzymes, and neurotransmitters actually run well. A 2025 Yale study supports the upward pressure on those numbers, finding that a cutoff of 25 ng/mL better identifies iron deficiency in women of childbearing age than the WHO's current 15 ng/mL threshold, and establishing a median ferritin of 59.5 ng/mL among iron-sufficient women. Ferritin below 30 to 40 ng/mL is frequently associated with debilitating fatigue even when hemoglobin reads normal, and the hair loss and restless legs literature points to targets above 70 to 80 ng/mL and 50 ng/mL respectively. The conventional lower limit was built to catch frank anemia at its most obvious, not to mark the level where tissues perform.
Ferritin is the body's main iron storage protein: it's a large spherical shell that holds iron and lets it go as cells need it. That iron goes toward mitochondrial energy production, oxygen transport in red blood cells, DNA synthesis, thyroid hormone metabolism, and neurotransmitter production. A lab report that calls a ferritin of 14 ng/mL "normal" for a premenopausal woman is reading off a number anchored to population averages, not to the level at which hair follicles, mitochondria, and thyroid enzymes actually function. That 14 ng/mL result sits inside the standard range and is, at the same time, almost universally associated with significant fatigue, hair loss, and impaired cellular function. Both things are true at once, and the reference range was never built to resolve the contradiction.
The lower limit exists to catch frank anemia. The upper limit is there to catch hemochromatosis and other iron overload conditions. Everything in between those two flags gets labeled "normal," regardless of whether it supports aerobic capacity, cognitive clarity, or a full head of hair. A range built to detect disease at its extremes says nothing about the much larger territory in the middle, where a person can score low enough to feel the effects of poor iron status but high enough to clear the bar that would prompt a doctor to act. Recognizing that the range was built for diagnosis, not performance, is the starting point for everything that follows.
How iron depletion progresses silently before hemoglobin falls

Iron deficiency does not announce itself in one step. It moves through three stages, and the standard blood panel is only built to catch the last one.
In stage one, your body starts to draw down its iron reserves, but your serum iron and your hemoglobin still read normal. Ferritin is the marker that moves first here, and transferrin, the protein that binds and transports iron, often rises at the same time as a compensatory response. Training adaptation and cellular repair are already suffering at this stage, as research on runners' performance shows, even though nothing on a basic panel would suggest a problem.
Stage two is where most symptomatic people actually live. Reserves are critically low. You feel fatigue set in, your workouts feel harder than they should, and your recovery slows down. Your hemoglobin is still technically normal, so a standard panel comes back clean and you get told there's nothing wrong.
Stage three is when the damage appears on a conventional lab test. At this point both iron stores and oxygen-carrying capacity are compromised, so hemoglobin drops and an anemia diagnosis appears on paper. By then, tissues and performance have been absorbing the damage for weeks or months.
The cellular explanation for why this takes so long to show up on bloodwork: iron is a required cofactor for mitochondrial complexes I, III, and IV, the machinery inside the electron transport chain that produces usable energy. When your ferritin drops below the functional threshold, functional medicine ferritin reference data shows your aerobic energy production starts to suffer before your red blood cell counts ever move. Ferritin functions like a detailed ledger of iron reserves. Hemoglobin only reflects the checking account balance, and that balance is the last number to change.
What ferritin does downstream: energy, hair, thyroid, and cognitive function
Low ferritin produces a strange, scattered list of symptoms, fatigue, hair shedding, brain fog, cold intolerance, restless legs, mood changes, and that list is wide because iron sits at the center of so many unrelated cellular processes. Someone with mildly low ferritin can present as stressed, aging, or simply "off," and get no clear diagnostic signal pointing back to iron.
Your energy and fatigue trace back to those same mitochondrial complexes. Iron is required for complexes I, III, and IV, and ferritin below 30 to 40 ng/mL frequently causes debilitating fatigue even when hemoglobin looks normal, functional medicine ferritin reference data shows.
Hair loss follows a similar logic. Hair follicles are among the most metabolically demanding tissues in the body, and they're among the first to get cut off when iron runs marginal. Ferritin below 30 ng/mL is strongly linked to telogen effluvium in women, and functional medicine and dermatology sources suggest targeting ferritin above 70 to 80 ng/mL for optimal regrowth.
Thyroid function depends on iron too. Thyroid peroxidase, the enzyme responsible for synthesizing thyroid hormone, needs iron to work. Low ferritin impairs hormone production and the conversion of T4 to T3 directly. Someone can develop hypothyroid symptoms while their TSH reads perfectly normal.
Cognitive function and mood run on the same supply line. Dopamine and serotonin synthesis both require iron, and low ferritin is linked to brain fog, depression, anxiety, and difficulty concentrating, especially in women of reproductive age.
Restless legs syndrome is one of the more treatable consequences. Low ferritin is among its most common causes, and ferritin below 50 ng/mL is strongly associated with how severe the symptoms get.
Exercise performance closes the loop. Oxygen delivery to working muscle depends on iron, and ferritin below the functional threshold measurably impairs VO2 max, endurance, and recovery.
Taken together, these are one story about a single mineral touching mitochondria, hair follicles, thyroid enzymes, neurotransmitters, and muscle oxygenation at the same time.
What ferritin level is actually optimal for energy, not just "normal" according to lab ranges?
A 2025 Yale study gave this problem a sharper number. The study found that a ferritin cutoff of 25 ng/mL better aligns with clinical and population data for women of childbearing age than the World Health Organization's current cutoff of 15 ng/mL, identifying iron deficiency earlier without a meaningful rise in false positives. The researchers established a reference interval of 19.7 to 133 ng/mL for iron-sufficient women, with a median of 59.5 ng/mL. That median sits far above what you'd count as adequate if you used a 15 ng/mL cutoff.
| Group | Conventional range (ng/mL) | Functional medicine optimal (ng/mL) | |---|---|---| | Women, premenopausal | 12 to 150 | 50 to 100 | | Women, postmenopausal | 12 to 263 | 50 to 100 | | Men | 24 to 336 | 70 to 150 | | Hair loss target (any sex) | n/a | above 70 to 80 | | Restless legs target | n/a | above 50 to 75 |
A woman with ferritin at 30 ng/mL clears the conventional lower limit of 12 by a comfortable margin. She still sits well under the 50 to 100 ng/mL functional medicine target, and squarely inside what amounts to a suboptimal zone, 30 to 49 ng/mL for women, 40 to 69 ng/mL for men, where a lot of symptomatic people land. They're above the line that gets flagged and below the level where tissues run well. The conventional lower limit was never meant to mark that second line, but now the Yale data gives it a specific number.
Populations for whom the gap between normal and optimal is most consequential
Some groups land in the suboptimal zone far more often than others, and recognizing the pattern is useful for anyone trying to figure out whether their own fatigue or hair shedding might trace back to iron.
Menstruating women carry the largest burden here. Monthly blood loss is the single most common driver of chronically low ferritin. The Yale study built its cohort around women of childbearing age because current cutoffs underdiagnose iron deficiency in this group more than in any other.
Endurance athletes face a separate mechanism. Running depletes iron through foot-strike hemolysis, gastrointestinal blood loss, and sweat losses, and iron-dependent mitochondrial enzymes cannot produce aerobic energy efficiently once ferritin drops into the suboptimal range. A runner can lose training quality and race performance at a ferritin level well above the conventional lower limit, long before any lab would call it deficiency.
Vegetarians and vegans face a bioavailability problem rather than a quantity problem. Plant-based diets give you non-heme iron, and your body absorbs it less efficiently than the heme iron you get from animal sources. Dietary iron intake that looks adequate on paper does not guarantee ferritin adequacy in the bloodstream.
Your iron demand rises a lot during and after pregnancy, so if you're pregnant or postpartum, the gap widens quickly while your stores may not keep pace.
Regular blood donors deplete their reserves on a schedule that diet alone often can't match. In population research on donors, 87.7% of female blood donors showed reductions in ferritin levels over repeated donations, a reminder that donation frequency deserves monitoring rather than assumption.
High ferritin and the upper-end risk
A high ferritin result is not automatically good news, and treating "higher" as uniformly better misreads what the number can mean. Ferritin above 300 ng/mL in men or 200 ng/mL in women may point toward hemochromatosis, a genetic condition that is more common than most people assume. Crossing those thresholds is the point where HFE gene testing, transferrin saturation testing, and liver function evaluation become appropriate next steps, functional medicine ferritin reference data indicates.
The underlying danger is oxidative stress. Excess free iron in the body drives free radical production, and that process damages cell membranes, DNA, and mitochondria, accelerating biological aging, longevity medicine framing holds. Iron is useful precisely because it's chemically reactive, but that same reactivity turns harmful once your stores run too high.
Interpreting high ferritin gets more complicated because ferritin behaves as an acute-phase reactant. It rises non-specifically with infection, inflammation, liver disease, metabolic syndrome, and malignancy, independent of how much iron the body actually has stored. If you deal with active inflammation, you can post a high ferritin number while your true iron stores remain genuinely depleted underneath it. One number can mean two opposite things depending on what else is happening in the body at the time, which makes a high result just as capable of misleading someone as a low one.
Reading a ferritin result accurately requires the surrounding panel
Ferritin alone, read in isolation, can point a person in the wrong direction in either direction: inflammation can mask real deficiency behind a falsely reassuring number, or inflammation can mimic overload where none exists. The only way around that is to read ferritin alongside the rest of the iron panel.
The full iron panel includes serum ferritin, serum iron, total iron-binding capacity (TIBC), transferrin, and transferrin saturation. Each piece measures something different. Serum iron fluctuates by the hour and by what you've eaten recently, so a single reading says little on its own. Ferritin reflects the size of the stored reserve. Transferrin is the transport protein that carries iron through the bloodstream. Transferrin saturation shows the working ratio, how much of that transport capacity is actually being used at a given moment.
Read together, these markers reveal the pattern that defines early-stage deficiency most clearly: ferritin running low while hemoglobin and serum iron still look normal. That pattern is the signature of stage one or stage two iron depletion, the stage where a standard panel alone would say everything is fine. A single ferritin number, considered without TIBC, transferrin, and saturation sitting next to it, leaves out the context that turns one data point into an actual diagnosis.


